
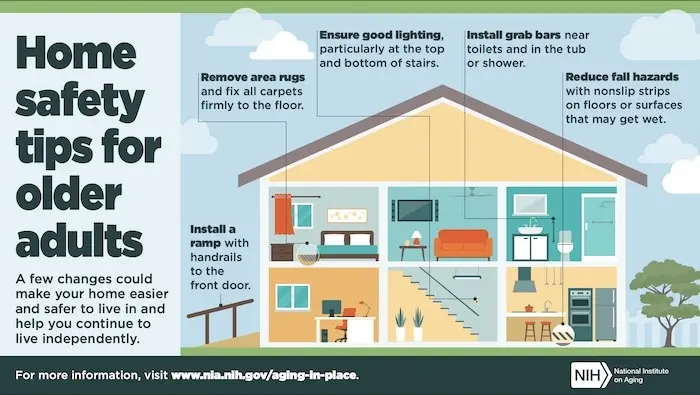
Over 80% of older adults express a strong, clear intention to age in place within their own communities and residences. However, a stark and challenging reality underpins these retirement plans: approximately 90% of American homes are completely unequipped to safely house them. Without immediate, deliberate home modifications, the desire to stay at home transforms quickly from a comforting prospect into a massive personal and financial liability.
The financial and physical arguments for modifying a home to meet the needs of aging residents have become increasingly difficult to ignore. According to the 2025 CareScout Cost of Care Survey, the national median cost of an assisted living facility has surged to $74,400 annually. Meanwhile, a private room in a nursing home exceeds $129,000 per year. Investing a fraction of those substantial sums into proactive structural safety measures can keep seniors independent, safe, and entirely out of overpriced institutional facilities.

Furthermore, ignoring common home hazards virtually guarantees a dangerous and costly emergency room visit. The Centers for Disease Control and Prevention reports that one in four Americans aged 65 and older falls each year. These incidents are rarely minor stumbles. The average treat-and-release emergency room visit for a senior fall costs nearly $8,900. Moreover, falling once doubles the risk of experiencing a subsequent fall, creating a dangerous cycle of injury that frequently forces aging adults out of their homes permanently.
For families looking to mitigate these risks, safety experts advise starting with the highest-risk zone in the residence: the bathroom. Nearly 80% of seniors eventually require targeted modifications, such as walk-in showers and strategically placed grab bars, to maintain their personal hygiene routines safely. Experts warn against relying on temporary suction cup handles, which are notorious for failing under full body weight. Instead, safety equipment must be hard-mounted directly into the wall studs. Families should also focus on eliminating everyday trip hazards by removing loose throw rugs and installing zero-step entryways wherever possible.
Beyond the bathroom, poor lighting is another critical environmental hazard that poses significant danger to older adults. As vision deteriorates naturally with age, standard overhead lighting quickly becomes insufficient, turning the navigation of a dark hallway at 2:00 AM into a recipe for severe injury. Research analyzing data from the National Health and Aging Trends Study shows that visual impairments, when combined with hidden home hazards, dramatically increase the risk of catastrophic falls.

To combat this, specialists recommend installing motion-sensor pathway lighting along every corridor between the bedroom and the bathroom, avoiding manual switches that require fumbling in the dark. Baseboard-level LED strips that activate upon detecting movement provide immediate visual cues without blinding the resident. Clinical settings have shown that upgrading to proper circadian-rhythm lighting can reduce falls among seniors by over 40%, underscoring the necessity of aggressively illuminating living spaces to compensate for aging eyes.
Kitchen accessibility presents another major hurdle for older adults. Standard kitchens are built exclusively for able-bodied adults, meaning that for a senior with declining mobility or someone utilizing a wheelchair, traditional kitchen layouts can become actively hostile. Aging adults facing arthritis or balance issues should not be expected to climb step stools to reach top shelves. Remodeling efforts must systematically remove these barriers by installing pull-down shelving hardware in upper cabinets so items can be accessed without straining or reaching.
For wheelchair accessibility, lower cabinet doors and base structures under the sink and primary food preparation areas must be removed to allow a chair to slide directly underneath. While private residences are not legally required to comply with Americans with Disabilities Act codes, ignoring their structural measurements virtually guarantees that the kitchen will eventually become unusable. Additionally, swapping out traditional cabinet knobs for D-shaped pulls can significantly ease the strain on arthritic hands.

Relying solely on physical check-ins from family members or home health aides is an increasingly outdated and risky strategy. Integrating smart home technology provides a reliable safety net that operates around the clock without demanding constant human oversight. Voice-activated smart thermostats and lighting systems ensure that aging adults never have to manually adjust difficult dials or risk a fall just to manage their immediate environment.
Furthermore, modern personal emergency response systems and medical alert devices have evolved far beyond legacy panic buttons that require a fallen senior to manually press them. Modern smart home monitors and wearable technologies utilize advanced algorithms to automatically detect falls, unusual behavior patterns, or sudden drops in mobility. If an emergency occurs, these connected systems can bypass the user entirely to alert caregivers or emergency services directly, bridging the gap left by traditional monitoring methods.
Despite the proven efficacy of these updates, financial assistance remains a major roadblock for many households. Homeowners hoping that Medicare will bridge the gap and help pay for necessary modifications face a grim landscape. Currently, only a tiny fraction of Medicare Advantage plans—about 6.2%—offer any partial coverage for structural home modifications. Original Medicare generally classifies grab bars, pull-down shelving, and wheelchair ramps as home improvements rather than durable medical equipment, leaving families to fund these vital updates privately.
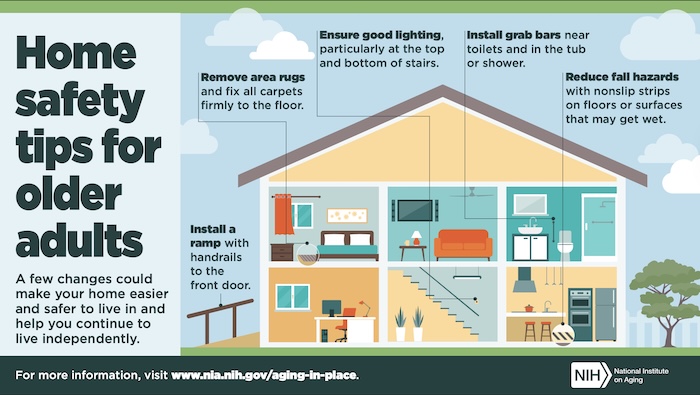
Ultimately, aging in place functions as an active, structural defense strategy rather than a passive state of being. Hoping for the best without making concrete physical changes to the living environment virtually guarantees a catastrophic fall and an involuntary transition into expensive institutional care. Viewing stud-mounted grab bars, motion-sensor lighting, and automated fall detection technology as non-negotiable medical interventions rather than optional home improvements can mean the difference between prolonged independence and a forced loss of autonomy.



