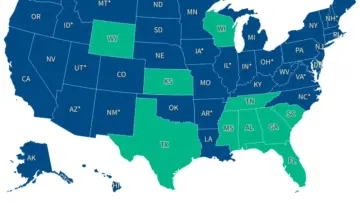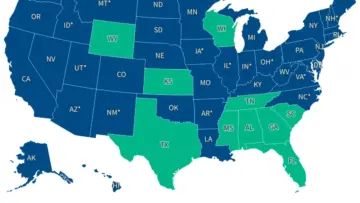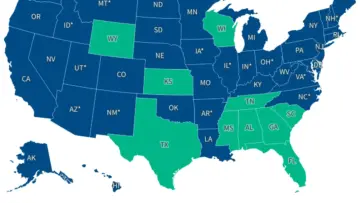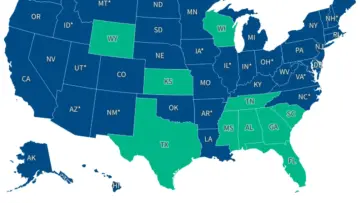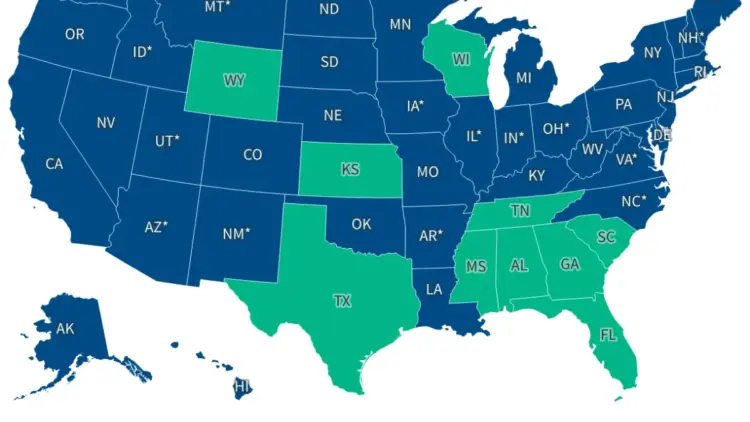
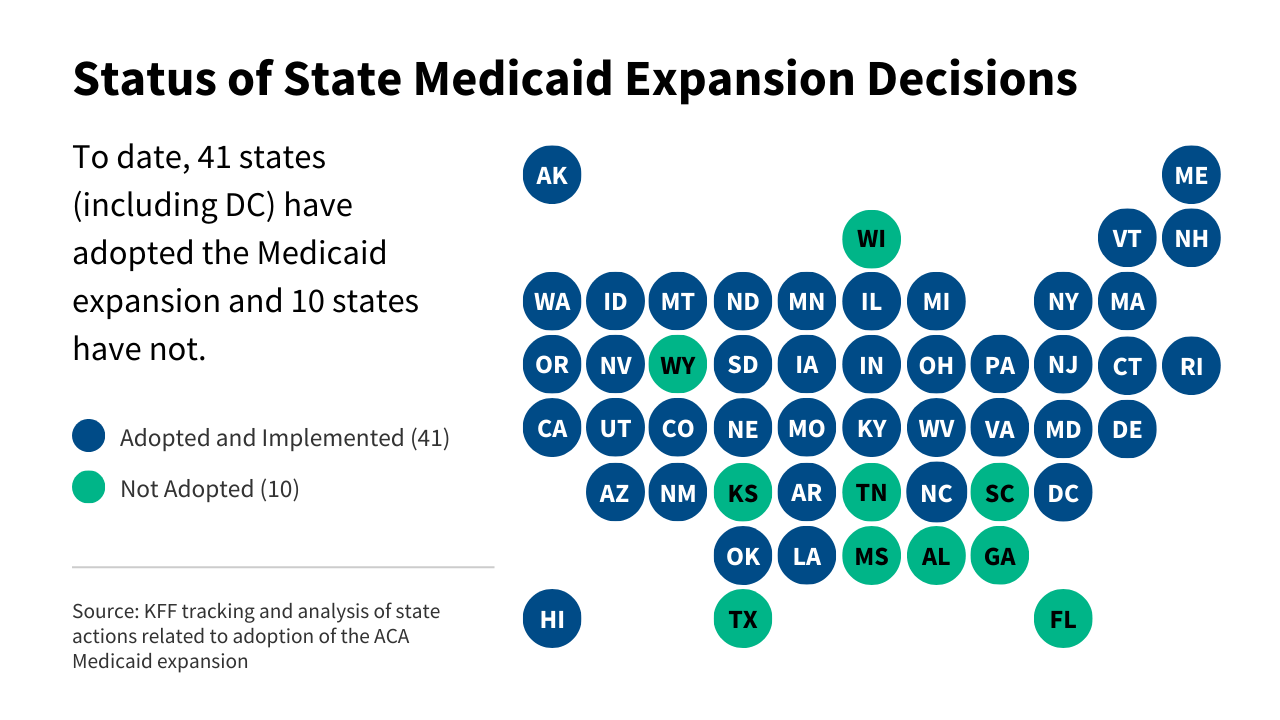
More than a decade after the landmark implementation of the Affordable Care Act, the national landscape surrounding its Medicaid expansion continues to evolve, reflecting a complex interplay of state-level politics, fiscal planning, and ongoing healthcare debates. According to the latest tracking and analysis from KFF, a total of 41 states, including the District of Columbia, have now adopted the ACA Medicaid expansion. Meanwhile, 10 states have chosen not to move forward with the expansion, leaving a distinct geographic and political divide in healthcare coverage across the country.
The ACA’s Medicaid expansion fundamentally transformed the nation’s healthcare safety net by extending health insurance coverage to nearly all adults with incomes up to 138 percent of the Federal Poverty Level. For an individual, that income threshold translates to $21,597 based on the 2025 federal poverty guidelines. In addition to broadening the scope of eligibility, the federal law incentivized state participation by providing an enhanced federal matching rate, commonly referred to as the FMAP, covering a substantial majority of the costs for the newly eligible expansion populations.
Despite the federal financial backing, adoption has remained a state-by-state decision, resulting in a persistent patchwork of policies. KFF’s comprehensive tracking provides an ongoing look at state expansion activity, illustrating where policies stand through detailed state indicators and interactive maps. While the majority of states have embraced the program, the remaining holdouts continue to experience vigorous domestic debates, legislative maneuvering, and alternative proposals regarding healthcare access for low-income residents.
The current status of state actions highlights the dynamic nature of these healthcare policies. In non-expansion states, policymakers and advocates frequently revisit the issue through various avenues. These non-expansion tracking efforts capture legislative actions, such as the formal passage of expansion bills in at least one legislative chamber or committee, as well as executive actions including gubernatorial budget proposals, executive orders, and significant administrative announcements. Furthermore, voter-led initiatives have played a critical role in several states, where grassroots campaigns have successfully pushed the expansion question directly to the ballot box, bypassing reluctant legislatures.
In some non-expansion states, discussions have also encompassed limited coverage expansions. However, researchers and policy analysts emphasize that these restricted programs do not qualify as full ACA Medicaid expansions and, crucially, do not qualify for the enhanced federal matching funds that accompany full compliance with the federal statute. These alternative approaches generally provide restricted benefits to smaller subsets of the population rather than comprehensive coverage up to the 138 percent poverty threshold.
Conversely, the landscape within states that have already adopted the Medicaid expansion is also shifting. Recent state actions in expansion jurisdictions frequently focus on placing new limits, restrictions, or administrative requirements on the expansion population. States often pursue these policy adjustments through Section 1115 demonstration waivers, which allow them to test new approaches within their Medicaid programs, such as work requirements, premium contributions, or enhanced reporting mandates, subject to federal approval.
Adding another layer of complexity to the national dialogue are recent legislative activities surrounding so-called "trigger laws." These statutory provisions tie the continuation of a state’s Medicaid expansion directly to the specific share or level of federal funding provided by Washington. If federal matching rates were to decrease or face substantial cuts, these trigger laws are designed to automatically scale back or terminate the expansion, potentially resulting in the sudden loss of health coverage for millions of residents.
State-level engagements with these trigger mechanisms have varied considerably. South Dakota and West Virginia, for example, have considered or implemented actions to put such trigger laws in place, reflecting caution regarding future federal fiscal commitments. In Virginia, a notable budget amendment was introduced to remove the automatic termination of the expansion from the state’s trigger law framework. Instead of an automatic cutoff, the proposed amendment would have required a legislative committee to develop thoughtful recommendations on how the state might adjust to any potential future loss of federal funding. Although the amendment was ultimately not included in the final budget, it underscored the growing legislative anxiety surrounding federal funding stability.
Similar policy friction has emerged in other parts of the country. Proposals aimed at completely removing or scaling back existing trigger laws have been introduced in states such as Illinois and North Carolina. These legislative efforts reflect an ongoing tug-of-war between lawmakers who view trigger mechanisms as essential fiscal safeguards against federal budgetary shifts and those who view them as an unnecessary threat to the continuous health coverage of vulnerable populations.
As tracking organizations like KFF and academic institutions like the Georgetown Center for Children and Families continue to monitor these developments, the future of the ACA Medicaid expansion remains a central focal point of American healthcare policy. Whether through fresh legislative pushes in non-expansion states, ongoing waiver negotiations in established expansion states, or high-stakes debates over federal funding triggers, the state-level decisions surrounding Medicaid will continue to shape the contours of healthcare access for millions of Americans nationwide.